
Fetal Heart Rate Interpretation: The Starting Point
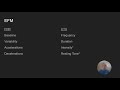
Intrauterine resuscitation begins with a systematic evaluation of the fetal heart rate (FHR) and uterine contractions. Use the four categories for each:
Fetal Heart Rate Components
- Baseline
- Variability
- Accelerations
- Decelerations
Uterine Contraction Components
- Frequency
- Duration
- Intensity (palpate or use internal monitors)
- Resting tone (palpate between contractions)
Understanding the FHR Categories
The standardized three-tier system guides clinical decision-making. For a deeper review of the specific waveform components, see Fetal Heart Tone Monitoring: Accelerations & Decelerations Explained.
Category I: Reassuring (Green Zone)
- Normal baseline (110-160 bpm)
- Moderate variability
- No concerning decelerations (early decelerations allowed)
- Accelerations present but not required
- Action: No intervention needed; may continue monitoring or discontinue.
Category II: Indeterminate (Yellow Zone)
- Everything between Category I and III
- Examples: Tachysystole, minimal variability, deep variables
- Action: Watch closely and prepare for intervention; these patterns can deteriorate if uncorrected.
Category III: Emergency (Red Zone – Fix or Deliver)
- Absent variability PLUS recurrent late or variable decelerations
- Fetal bradycardia (baseline < 110 bpm)
- Sinusoidal pattern
- Prolonged deceleration not returning to baseline
- Action: Immediate intervention or move toward delivery within 30 minutes.
Pro Tip: If you can’t remember all criteria, focus on: Category I = happy baby; Category III = emergency; Category II = everything else requiring action.
The VE CHOP Mnemonic: Identifying the Cause
This mnemonic links FHR patterns to their underlying causes. Understanding the terminology used here is crucial, review Nursing 351 OB Terminology: Gravida, Para, Trimester & Abbreviations for essential definitions.
- V – Variable Decelerations → Cord compression
- E – Early Decelerations → Head compression (usually benign in labor)
- C – Accelerations → Good fetal oxygenation (reassuring)
- H – Late Decelerations → Placental insufficiency (always requires intervention)
- O – (Not a separate category – the “O” in CHOP completes the mnemonic)
Clinical Pearl: Early decelerations in a non-laboring preterm patient may indicate unexpected cervical change, check for dilation.
The POISON Mnemonic: Intrauterine Resuscitation Interventions
Apply these interventions systematically, using critical thinking to select the right ones for the specific FHR pattern:
P – Position Changes
- Goal: Improve uteroplacental perfusion, relieve cord compression
- Left lateral is the default (anatomically optimal)
- If ineffective, try right side or other positions
O – Oxygen
- Current practice: Use only if maternal SpO2 < 95%
- Historically: Hyperoxygenation to improve fetal oxygenation
- Still tested on NCLEX, but clinical evidence now discourages routine use
I – IV Fluid Bolus
- Goal: Increase perfusion to uterus (correct hypotension, especially from epidural)
- Contraindicated: In hypertensive patients (risk of fluid overload)
S – Spec/Speculum Exam (Sterile Vaginal Exam)
- Look for: Cord prolapse, vaginal bleeding, rapid cervical change
- Essential if sudden severe variables or non-reassuring pattern appears
O – Turn Off Oxytocin (if running)
- First-line intervention when tachysystole or fetal intolerance is present
- Can be restarted once fetal status improves
N – Notify Healthcare Provider
- Always at the end because nursing interventions should be tried first
- Call to report: “This happened, I did X, Y, Z, and the result is ____. I need your input.”
Critical Thinking: Applying the Right Interventions
Not all interventions fit all situations. Match the cause to the fix. For a clearer understanding of how fetal positioning interacts with labor management, see Fetal Station Explained: Understanding Baby's Position in the Pelvis.
Case Example 1: Fetal Tachycardia
- Tracing: Baseline 185, moderate variability, accelerations, no decels
- Likely cause: Maternal fever/infection
- Appropriate interventions:
- ✅ Position change – NOT indicated (no perfusion issue)
- ✅ Oxygen – NOT indicated (variability is good)
- ✅ IV fluids – Indicated (replace insensible loss from fever)
- ✅ Spec exam – NOT indicated (no prolapse/bleeding risk)
- ✅ Turn off oxytocin – NOT indicated unless variability drops or decels appear
- ✅ Notify – Only if fever is new/undiagnosed (possible chorioamnionitis)
Case Example 2: Late Decelerations with Minimal Variability
- Tracing: Baseline 145, minimal variability, no accelerations, late decels with 2/3 contractions, tachysystole (contractions q3-4 min, 80-90 sec), oxytocin running
- Likely cause: Uteroplacental insufficiency from hyperstimulation
- Priority interventions (order matters):
- Turn off oxytocin – immediately
- Position change – left lateral
- IV fluid bolus – unless patient is hypertensive
- Oxygen – only if maternal SpO2 < 95%
- Spec exam – not indicated (no prolapse/bleeding suspicion)
- Notify provider – after above interventions, report status
Golden Rule: For nursing exams and practice, always attempt independent nursing interventions before calling the provider. Summary: P-O-I-S-O-N actions first; N (notify) last.
For additional context on tracking fetal growth alongside these monitoring parameters, refer to Fundal Height Measurement: Maternity Nursing Review for NCLEX.
All right. So, this is intrauterine resuscitation mini lecture. Um, I'm adding my face down here. I had a
request that um it would be helpful to see me talking when we do the mini lectures. Uh, so I'm going to try to
incorporate that for the ones that um I can. Um, it won't be all of them, but I'll try my best. Uh, so when we talk
about intrauterine resuscitation, we have to remember that we always start with interpretation of our fetal heart
rate and our contraction. just like we talked about in the last mini lecture in class. Um so our fetal heart rate we
have four categories baseline variability accelerations decelerations and then for our contractions we also
have four categories frequency duration intensity and then our resting tone. resting tone is going to require our
hands to be on the abdomen on the belly uh to palpate in between contractions and that intensity um we're going to ask
the patient for subtractive and then if we are not using internal monitors which more than likely we aren't those are
less frequent uh we will be palpating during the contractions to palpate intensity.
So keeping in mind we always have to start with our interpretation. And when we talk about what's normal or
abnormal uh within the fetal heart rate, we have categories. This is a standardized process. Categories that
tell us um what to do next or how concerned we need to be in regards to what we're seeing on the fetal monitor.
Um so category one all the way over to the right where it's green. Everybody's happy. It's reassuring. We have a normal
baseline. We have moderate variability which is what we want and we don't have any concerning decelerations meaning if
we do have decelerations it's usually like an early which we know are not concerning. Um we don't have tachiscy of
the uterus. We don't have deep variables. We don't have late decelerations. We can have accelerations
because that's a positive thing but it's not um we don't jump into action if we don't have accelerations. So, it's great
if we see them. We don't freak out if we don't see them for a little while. So, that's our category one. Um, and
depending on the patient situation, that might be like we're satisfied and we get to take the patient off the monitor
completely or if they still need to be like we have a reason to continue monitoring them just in case something
changes, then we continue monitoring, but we don't have to intervene, we don't have to do anything else different.
Category two is our um indeterminant category. So this is the keep watching and we likely might be doing some kind
of intervention. Now what that intervention is is variable. It might be very something very minimal. It might be
something more intense. Um but it's the ones where we see concerns in the fetal heart rate whether that's in response to
contractions in labor or not. Um but it's something that tells us like we're not completely category 1, but it's not
so bad that we need to do something like eently which puts us in category 3. So, this might be, for example, um the
patient's having more contractions they would like than we would like them to. Maybe we have them on ptocin and they're
contracting more than five times every 10 minutes or they only have 30 seconds of resting tone between contractions or
um baby is starting to show some really deep variables with every contraction. We used to have moderate variability and
now we're down to minimal. um those kinds of changes to which we know if we don't do something to fix them over time
they will lead to baby losing its reserve and put us closer to that category 3 or do something that changes
us to category 3. So we don't we don't just sit on a lot of those things and watch them happen and not do anything
because if we don't do anything then we're going to end up in a worse situation later. Category three then is
um evidence of changes in the fetal heart rate that mean we are in emergent
situation now we either need to fix the problem immediately or we need to be moving towards delivery in the next 30
minutes or less. This is our fix to deliver fix or deliver category. Um, and even if you can't remember all of the
things that go in each category, um, because especially if you look up the individual criteria for category 2, it
has so much in it. Um, if you can remember the fix or deliver, it's an emergency situation, or everybody's
happy and everything's reassuring, and then just remember that everything else falls in the middle. Um, so unless we
have a perfectly happy strip of which we know we don't need to do anything or a catastrophically bad strip to which we
have minutes to do something about it or we end up with a poor outcome, everything else falls in the middle into
that category too. So, um, backing up to category 3 that that fix or deliver things that would constitute that. Um,
if we have an absent variability, that's bad all around. Um, but if we we need to still couple that with something else
terrible. If we have absent variability out of a baby um but nothing else, that still actually puts them in category 2.
Are we going to do something about it? Absolutely. Are we going to rush them to the O? No. But if we have absent
variability and we're starting to see lates with more than just sporadically, like recurrent contractions, if we are
seeing absent variability with recurrent variables that are significantly deep, we're going to do something about that
really quickly. um fetal brada cardia. So a fetal heart rate baseline of less than 110 um consistent we would we would
be very concerned about that. That is not the same for tacocardia. Fetal tacoc cardia while it is concerning and while
we will do something about it or look for the reason that it's there um we can we can handle tacocardia brada cardia is
detrimental. So those aren't always um some people like to put those in the same category and they're completely
different. The the reason for that being the cause of fetal brada cardia is completely different than the cause of
fetal tacoc cardia for very very different um very different causes very different outcomes for the fetus uh very
different interventions based on what we would do to fix it. Um other things that would constitute a category 3 sinosoidal
pattern big deal. um we will talk about a little bit in class what that looks like and it's not a super common
occurrence and it means very detrimental things if it's true sinusal. Um and then if we have an abrupt deceleration that
ends with um whether it's a prolonged deceleration that we can't get to come back up to baseline or it's a prolonged
acceleration that ends up leading to fetal brada cardia which would put us back up to to category 3. All of those
things would be like a we need to fix or deliver right now. Um I will not say that
every how do I put that? Sometimes we have a category 2 strip but it's a severe enough category 2 where we're not
to category 3 like we have to fix it within the next few minutes but we're not going to sit and let the patient
labor for much longer than that. Um and we'll go through some strips in class as to what that looks like and what those
things would be. Um, but this is the categories we use and it's very um consistent terminology. The that way
that all um when we look at research that tells us what the evidence-based practice is for whatever the fetal strip
shows us, uh we default to this because it keeps it consistent and it keeps us um supporting patients or intervening
when we need to in a way that we know promotes best outcome. So, the ve chop pneummonic, um, if
you've seen this, great. If you've talked about it with somebody, awesome. If we've already covered it in class,
fantastic by the time you watch this. Um, the veh chop pneummonic isn't going to, um, it doesn't tell you what all to
do when you see a change in the fetal heart rate. But if you can remember the vehop pneummonic, you can, it
essentially tells you what's causing the change that you're seeing. And if you know what's causing the change, you know
how to intervene for the cause. So variable D cells, the ones look like a V, really sharp down, really sharp
increase back to baseline, those are caused by cord compression. So that means the umbilical cord for whatever
reason is being compressed. Whether that be it's around baby's neck and that's being compressed. Whether that be it is
positioned between baby and the uterine wall and when the contraction happens, it's pressing on that cord. um whatever
that might be, something is pressing on the cord, compressing the cord and that pressure um that change in pressure and
change in blood flow stimulates the barrel receptors which is deeper than a level you need to know but within the
fetus that causes it to change its heart rate in reaction. Um so if we know it's chord compression, we
see a variable, we know chord compression uh is the cause, we know how we can fix it. Um early decelerations,
that's your E in the veto. Uh early decelerations are caused by head compression. So these are lined up. What
causes them? Head compression causes our early decelerations. So if we see early decelerations and our patient is in
labor and we know the fetus is head down with its head in the cervix um or you know in the birth canal in the pelvis,
it's not illogical to think that their head might be compressed at some point. Like that's absolutely going to happen.
So when we see early decelerations and we know they're caused by a head compression if we are well aware that
our patients in labor, we don't we don't have to do anything about about early D cells. We document
them and we move on. Um they're not concerning, they're not detrimental, it's not going to lead to hypoxia for
the fetus. The only time I would I have ever been any bit concerned about early decelerations is if I have a like
pre-term high-risisk patient who is there um either outpatient like coming in for a visit or inpatient because
we're monitoring them and we have them on the monitor even for just an ST and they throw out a couple contractions and
baby has head compression and early D cells with each contraction. That is a patient that is not in labor. I prior to
that didn't think that baby's head was low enough for that to happen. Um that might be something that warrants
additional assessment just because why is that baby's head so far engaged and is this patient in labor and we don't
know it kind of thing. It still doesn't mean that I'm concerned that the baby is lacking oxygen in any way or hypoxic in
any way. That would just be like ooh that's the only thing that causes those. Maybe we should check her. Maybe she's
dilated. Maybe she's in labor and we didn't know. Otherwise, if your patient's in labor and they're showing
early D cells, document, move on with life. Not concerning. No intervention needed. Um, accelerations are caused by
oxygenation. Oxygen is a great thing. We would love the fetus to be oxygenated. That's positive. So, when we see
accelerations, we document them. We move on. We're reassured that our baby is oxygenated. Great. Love that for
everybody. The L is for our late decelerations. This is one that is always, always, always bad. Always
requires intervention. Always requires documentation and notification. Late Dy cells are never a good thing. Lady Dy
cells are caused by placental insufficiency. That's the P in our chop. Um placental insufficiency can is a kind
of an umbrella term for a variety of things. It can be poor oxygenation to the placenta. It can be poor blood
profusion to the placenta. It can be a poorly operating placenta if especially if we're talking about like a post-term
um pregnancy or a um patient who has a chronic abruption situation or there are um sometimes with certain complications
such as like pree we have Doppler flow issues where like we know that the umbilical cord and the placenta the
blood flow doesn't always go the direction it should. The vessels aren't shunting to the appropriate spaces the
way they should. Um, it can mean any any of these things, but essentially bottom line, the placenta is not giving baby
what it needs. Whether that be perfusion, blood volume, whether that be oxygenation, whether that be taking um
waste away from baby, whatever it is, the placenta is not functioning as it should. So, that's our ve chop
pneumonic. And again, it doesn't tell you how to fix anything that you're seeing, but if you can remember how
those um causes line up to the changes, if you know the cause, you can identify how to fix it. So, that's the shop. And
then we have our next pneummonic. So this is our true intrauterine resuscitation pneummonic is our poison.
Um which I know is seems like kind of counterintuitive to think of the word poison when you're trying to fix
something. Um but that's what makes it so great. It's easy to remember. Uh so the P is for position changes and that
is position changing for mom. Uh so if we change mom's position in labor, that changes the pressure off the cord, for
example. or if the uterus is um blood flow isn't going the way we want it to and baby's looking funky and we switch
mom to her other side. Uh left side for mom is theoretically anatomically uh the position that should allow for
the most um blood flow the most perfusion to the uterus is on mom on our left side. Um, we know that because
anatomically it has to do with the the way the aorta and the vennea run. Um, and how that oxygenated blood makes its
way to the uterus. So, we know that anatomically, theoretically, left side is our go-to. I will say that, you know,
90% of the time that works and it's great and baby's happier when mom's on her left side. But, we know that there
are exceptions to every rule and it that doesn't change for fetal monitoring. It doesn't change for pregnancy. Um, so
sometimes you'll have mom on her left side and baby starts looking like crap and you flip her to her right and all of
a sudden baby looks better for whatever reason and that's fine. So it's not that we only have one position change we can
do. Um, left side is usually our go-to, but if left side isn't working, we will try a different position. Um, the
position change for mom can help with your blood flow. It can decrease cord compression. Um, it can make changes
that help support baby's perusion and oxygenation. Second or the first O there being
oxygen. Um, this is one that we still leave in here because it's on Inlex. This hasn't changed. It is still in
practice. Um, but evidence is leaning the other way for oxy hyper oxygenating mom. Um, if we don't have a specific
reason to do so. Okay. So for the purposes of this course and the purposes of our exams and the purposes of INLEX,
you're still going to incorporate that oxygen is a intrautin resuscitation measure. When you are in practice, when
you are in clinical um you will note if you see a baby strip that looks bad, as long as mom's oxygenation levels are
appropriate above 95% that we will no longer place oxygen on moms for intrigue or resuscitation.
Um, this actually kind of came about during COVID when everybody was very um cautious with the use of oxygen for
patients who could possibly have CO or had known COVID um to try to prevent um passing it to others that are taking
care of them. And there was research conducted and when we were not doing that that it wasn't really changing the
outcome for mom or baby. The previous thought was if we were hyper oxygenating mom, meaning um oxygen moves through the
placenta to baby bed passive diffusion. So if the oxygen concentrations in mom's blood were higher than what was in
baby's blood, even if those were not significantly different levels. So let's say mom's O2 saturation is 99%. But
theoretically baby's is 95. That that would still increase baby's oxygen even though both numbers were
okay, right? above what we would like. Um, so that was the theory behind it is if we could hyper oxygenate mom, it
would essentially pass some to baby and we weren't harming mom with the oxygen. Now we are through research is showing
that it really didn't make that much of impactful impact in the outcomes. So unless mom's
oxygen is lower than 95%. We don't usually use oxygen. Now, if mom is O2 sats are at 93, we're going to put
oxygen on her because that's that's out of our normal range and we want to um but for the purpose of this, we're still
going to consider oxygen as an intravenous resuscitation measure because not everything's caught up to
everything that it should. Um IV fluid bololis. So, this the the goal for this is to in increase perfusion by
increasing volume in the circulatory system. Um if we increase that volume, it increases profusion to uterus, which
hopefully helps our baby look better. Uh we also use this to correct maternal hypotension, especially if it's in
relation to um an epidural or spinal anesthesia cuz we know that's a side effect. Um the only patients who we get
I'll say is stingy or careful or maybe we don't include this one. um is if they are known hypertensive, if they are
already dealing with high blood pressure, we're not going to bully them with IV
fluids, at least not freely. Um we're going to be a lot more hesitant with those uh because we can make that
problem worse, right? And risk and benefit. Um S is for the speck and check. So this
is a sterile speculum exam or a sterile vaginal exam, one or the other depending on the patient situation. Most often
it's going to be a sterile vaginal exam. Um, and what we're looking for there is when we see certain changes on the
monitor, we think, okay, there are certain um, causes that could be causing the changes we're seeing. Some of those
causes are if the patient is having vaginal bleeding, if we're seeing changes that look like baby might not be
perusing well, do we have any vaginal bleeding that is pulling circulation and oxygen away from baby in the placenta?
Um, another is a cord prolapse. If we see a sudden variable that is super severe andor doesn't come back to
baseline, that could be caused by a severe chord compression. Did we drop a cord? Is the patient um is it possible
if she ruptured? Did she have a high station? Is there space for this cord to slip out? Um and we check for a cord.
The other thing we might see is um rapid descent of baby in labor. So let's say we have a mom who's been like 5 to 6 cm
and baby's looked great and all of a sudden we see some weird D cells and we're trying to figure out what's going
on. Um and we go to check her and she was 5 to 6 an hour ago and now she's 10 and complete and ready to push. And what
happened was she dilated really quickly and baby came down in the birth canal really quickly and now we're seeing the
the effects of that on baby um on the monitor. Now that doesn't always mean like that it's a bad thing like great
rapid descent and baby's ready to come out. But it does mean that we need all the people we need for delivery because
if baby's made that rapid descent then delivery is probably not far off. So that's one of the things that we just oh
we need to make sure that there's not a cord, there's not bleeding, there's not baby um that we weren't aware of. Um the
second O is turning off oxytocin or ptocin if it is running. If we have any changes on the fetal monitor that
indicate to us that baby is not tolerating labor um not tolerating contractions, losing their reserve um
and we have oxytocin running, we turn it off. If we are causing the situation that is impacting baby negatively, then
we stop causing that situation. Um, we can always turn it back on later once baby looks better, once they can
tolerate it. Uh, but we are we don't want to get to the point where we are causing a detrimental fetal heart rate
change that may or may not end up in emergency section in the O because of something we are giving mom to help her
progress in rel. And then the N is for notifying the healthcare provider. And it's at the end for a reason. Um
I've said many times nurses hold a lot of power and labor and delivery nurses hold a lot of autonomy and there's a lot
of ch um training that goes into understanding our role, understanding our scope, understanding the
interventions that we can do um independently. And when we have changes in the fetal
heart rate that warrant intervention, we need to try our nursing interventions first before we call the healthcare
provider if it's something we can fix because 90% of the time we have the interventions at our disposal that will
that will fix our problem. So usually by the time we get to notifying the provider, we are either saying, "Hey, uh
letting you know this happened. this is what we did and it fixed it but just wanted you to be aware this was the
situation or we are notifying because we are saying we had this change we have done XYZ we it's still happening we need
you to come lay eyes on the patient assess further and change plan of care whatever that might be um but if your
patient's having variable D cells and you call the provider and say she's having variable D cells with every
contraction 40 beats lower than baseline and they're going to say well what did you do about it.
Did you try to fix it? Um because we have interventions within our power that we should try first before before we get
to that point. Um so that's why we keep the N at the end. It's at the end because it's not your first intervention
for most things. There are a small small subset of circumstances in which there's not really much we're going to be able
to do to fix it. We need to call. Um but for the for the vast majority of changes, there are things we should be
doing first. If at the very least, even if we know we can't fix it, there are interventions we should do that will
support patient and baby and oxygenation and prevent hypoxia that we should put in place before we call to notify so
that we are not making the problem worse while we are changing the plan of care and moving forward. So ends at the end.
Um this brings me to critical thinking, right? We apply that to everything I
hope. Um and just because we have a whole list of intraven resuscitation measures does not mean that all of them
are always appropriate for every change that we see in the fetal heart rate. So we really need to think through the
rationale and the goal of each intervention that we want to apply so that we can identify which are indicated
for which change we're seeing. Um interventions should always be indicated supported by evidence. Um they should be
as minimally invasive, right? We we don't always jump to the most invasive, most severe intervention. We start we
start with the minimally and then we move our way forward. Um they should always be appropriate given the patient
situation. So just like I said with like an IV fluid bolis, that is absolutely an intervention for late decelerations.
But if my patient's blood pressure is already high, I am not going to overload them with fluids to try to fix a baby
problem cuz I'm going to make both problems worse eventually, right? If we're not profusing well, that's not
going to be helped by additional fluid. If we already have high blood pressure, we don't have a low blood pressure, low
profusion situation. Um, and then evaluated for response. Any intervention requires an evaluation. Whether it's
working, whether it's not, what do we do next? If it's not, what next steps need taken? Um, all interventions require
evaluation. So, to put that into context, um, an example, fetal heart rate baseline 185 with moderate
variability, positive accelerations, no decelerations. Patient's contracting every 5 minutes. Those contractions last
45 seconds to a minute. They're moderate in intensity and she is soft resting tone. So we know that the baseline 185.
That's fetal tacoc cardia. Okay. Uh we said 110 to 160 is our normal range. Fetal tacoc cardia most likely is caused
by a maternal fever. There are very few other things that can cause fetal tacocardia. It is almost always that mom
has a fever. Maybe she has an infection. Um but more than likely that's the cause. And I said fetal tacocardia is
notable. It's it it's worth paying attention to absolutely but it is not as um detrimental as fetal brain cardia. So
then when we look at our interventions position change not indicated for fetal tacoc cardia um we don't have a
profusion issue right we don't have a compression of the cord issue we don't have um an oxygenation issue because we
have moderate variability which tells us our fetus is well oxygenated and acceleration that tells us our fetus is
well oxygenated so we don't need oxygen. um an IV fluid bololis could absolutely help this patient. Not because it's
going to increase profusion, not because it's going to bring the fetal heart rate down to a normal baseline, but because
if the patient has a fever, which we are going to assess for, but more than likely that's our problem in this case.
Um they are going to have insensible fluid loss. They are going to lose fluid faster. So we definitely want them on
fluids absolutely because we need to replace what they're going to lose because of the fever. Um speck and check
not indicated for tacoc cardia oxytocin off. If we had oxytocin running on this patient if our variability was to
decrease or if we were starting to see decelerations then absolutely we would turn our ptocin off. But the fact that
we have moderate variability in ax cells with no d cells tacoc cardia in and of itself does not mean we need to turn the
ptocin off and change the plan. um notifying the healthcare provider. If the patient has a fever and we already
we haven't already diagnosed her with some type of infection, then that's concerning, right? Because that's a sign
of infection. Um if if the we're treating the patient for an infection and we have Tylenol ordered
that we can give her to bring down a fever and she has a fever, then we are going to give her Tylenol and try to
bring that down. And then more than likely, if we bring the mom step down, baby's heart rate's going to come down
and we'll be back in a normal range. So unless we have additional signs and symptoms of concern that are not already
diagnosed and or we have changes in the fetal heart rate that are concerning, then this does not require notification
because we there's nothing we're going to do to fix it other than what we're doing. Now again, if the patient has a
fever, we haven't diagnosed her with an infection. This is a new onset problem. she probably has cororeo and yes we need
to we need to identify that and and notify the doctor so we can get her antibiotics and and treat her like she
has cororeo. Um but if this is not a new new development this doesn't require any notification to anyone.
Another example um fetal heart rate baseline 145. We have minimal variability no axels late decelerations
with 2/3 of the contractions. She's contracting every 3 to four 3 to 4 minutes lasting 80 to 90 seconds.
They're strong to palpation. Her resting tone is still soft. We have ptocin running on this patient. Her protocol,
she has an epidural in place and her steraginal exam is 680 and zero. Um, so position changes. Yes, for this patient
absolutely position changes are indicated. We have late decelerations. We have placental insufficiency. Uh, we
want to try to improve our perusion to the placenta and a position change can help with that. So yes, let's stick this
patient on our left side. She's on her left side. Let's stick her in a different side. Change her position. Um,
oxygen possibly. What are the oxygen levels of patient? Um, do we think we can help that with hyper oxygenation?
Maybe if it's a profusion issues, you can maybe put that on. If the patient's oxygen levels 99 100, probably not going
to do much with it, right? Um, IV fluids possibly. We said profusion problem, placental insufficiency, fluids could
absolutely be warranted for this situation. Um however if again hypertensive patient not the right not
the right trial right um speck and check not indicated by these changes um we we this would not indicate we have a core
prolapse um more than likely we this is not a situation in which we have bleeding so that's probably not going to
be your cause it wouldn't hurt to look but unless there's a high risk for that otherwise probably would not be the
first guess um and this is not we know I mean unless the vaginal exam is change from what we just know. Six. The baby
did not make rapid descent. We're still at six. Um, oxytocin off. Absolutely. That should honestly be the first
intervention in this scenario. We have ptocin running. We have contractions that are frequent and lasting a pretty
long time. And baby is exhibiting signs that they are not tolerating it. We have late decelerations, poor profusion from
the placenta, and we have minimal variability, which means baby's oxygen reserves are decreasing. Um, so turning
the oxytocin off is 100% warranted in this situation. Um, notification. Yes. And this is going to look like we had
late recurrent late D cells with minimal variability. So, we turned the ptocin off and now baby looks like this and is
better or not. or we um turn the ptocin off, we change her position, we gave her some fluids, um and we're still having
late D cells and we can't get them to stop. We need you to come lay eyes on the patient and do something different.
Um but again, this is not one of those instances where we would call the provider and say, "Well, she has minimal
variability and late D cells. We didn't do anything yet. Like, we should do our interventions and try to
fix the problem." um even if it doesn't make the problem go away altogether, it still supports a better outcome than
allowing it to happen. Um so this is that's how we would handle that situation. And we're going to go through
more um examples in class and look at some strips and really put some context to what we're talking about. But this is
how we apply that critical thinking to what um resuscitation measures we have at our disposal and what we should do.
So that's it for this one.
Fetal heart rate tracings are categorized into three tiers: Category I (reassuring) requires no intervention; Category II (indeterminate) requires close monitoring and preparation for possible intervention; Category III (emergency) requires immediate intervention or delivery within 30 minutes. Use the green-yellow-red zone approach: Category I = happy baby, Category II = yellow zone needing watchful action, Category III = emergency with absent variability and recurrent late or variable decelerations.
VE CHOP links FHR patterns to their causes: V = variable decelerations indicating cord compression; E = early decelerations from head compression (usually benign); C = accelerations signifying good fetal oxygenation; H = late decelerations signaling placental insufficiency requiring intervention; O completes the mnemonic but does not represent a separate category. Use this to identify the underlying cause and apply appropriate intrauterine resuscitation interventions.
The POISON mnemonic guides nursing interventions: P = position changes (left lateral default); O = oxygen (only if maternal SpO2 < 95%); I = IV fluid bolus (contraindicated in hypertensive patients); S = spec/speculum exam to check for cord prolapse or bleeding; O = turn off oxytocin (first-line for tachysystole); N = notify healthcare provider last after attempting independent nursing interventions. Always apply critical thinking to match interventions to the specific FHR pattern.
For Category III (emergency) tracings with absent variability plus recurrent late or variable decelerations, fetal bradycardia (<110 bpm), sinusoidal pattern, or prolonged deceleration, immediately initiate intrauterine resuscitation using the POISON mnemonic. Prioritize turning off oxytocin if running, position the mother in left lateral, give IV fluids (unless hypertensive), apply oxygen if maternal SpO2 is <95%, perform a spec exam if indicated, and then notify the provider. The goal is to correct the cause within 30 minutes or move toward delivery.
The POISON mnemonic is designed to prioritize independent nursing interventions before calling the provider. By attempting position changes, oxygen, IV fluids, spec exam, and turning off oxytocin first, you address the immediate cause without delay. This approach is tested on NCLEX and in clinical practice because it shows critical thinking and proactive management. Notify the provider last with a structured report: what happened, what interventions were tried, and the current fetal status.
For fetal tachycardia with reassuring features (moderate variability, accelerations, no decels), the likely cause is maternal fever or infection. Appropriate interventions include IV fluids to replace insensible loss and notifying the provider if fever is new. Avoid position change, oxygen, and turning off oxytocin unless variability drops. For late decelerations with minimal variability and tachysystole, the priority is turning off oxytocin first, then position change and IV fluids—addressing uteroplacental insufficiency from hyperstimulation. Always match the intervention to the underlying cause.
Use the VE CHOP mnemonic whenever you identify a non-reassuring fetal heart rate pattern to determine the underlying cause. For example, variable decelerations suggest cord compression, prompting position changes to relieve pressure, while late decelerations point to placental insufficiency, requiring interventions to improve uterine blood flow like IV fluids and turning off oxytocin. This clinical tool helps you select the most effective interventions from the POISON mnemonic and is especially useful for NCLEX exams and real-time decision-making in labor and delivery.
Keep this summary
Save it to LunaNotes and it becomes a real note in your library — editable, searchable, and ready to turn into flashcards or a diagram. Free to start.
Save to LunaNotesOr summarise for another video.
This summary and transcript were automatically generated using AI with the Free YouTube Transcript Summary Tool by LunaNotes.
Related summaries
Intrapartum Nursing: Labor Stages, EFM Interpretation, and OB Emergencies
This comprehensive lecture summary covers essential intrapartum nursing concepts including true vs. false labor assessment, the four stages of labor with their phases, fetal heart rate monitoring interpretation (baseline, variability, accelerations/ decelerations), and critical obstetric emergencies like cord prolapse, shoulder dystocia, and amniotic fluid embolism. A must-review for nursing exams and clinical practice.

Intrapartum Complications: Cord Prolapse, Shoulder Dystocia & Emergencies
This video provides a critical overview of intrapartum complications requiring immediate intervention, including cord prolapse, shoulder dystocia, non-reassuring fetal status, postpartum hemorrhage, amniotic fluid embolism, uterine rupture, and placental abruption. Learn how to assess risks, identify signs, and implement prompt interventions to optimize outcomes for both mother and baby.

Intrapartum Assessment & EFM Interpretation: Focused Nursing Guide
This mini-lecture covers the five essential focused assessments for intrapartum patients: pain, contractions, leaking of fluid, vaginal bleeding, and fetal movement. Learn how to subjectively and objectively evaluate each component, including a practical palpation trick to gauge contraction intensity, and understand the critical importance of fetal movement as an indicator of fetal oxygenation.
Fetal Heart Tone Monitoring: Accelerations & Decelerations Explained
Learn the essentials of fetal heart tone monitoring, including normal heart rate ranges and how to interpret accelerations, early, variable, and late decelerations. This guide covers causes, nursing interventions, and key differences between monitoring types to help assess baby's status during labor.
Electronic Fetal Monitoring (EFM) Basics: External & Internal Methods Explained
This lecture provides a comprehensive overview of electronic fetal monitoring (EFM), covering external and internal monitoring methods for fetal heart rate and contractions. Learn to interpret key EFM components including baseline, variability, accelerations, decelerations, and contraction patterns like frequency, duration, intensity, and resting tone.
Most viewed summaries

A Comprehensive Guide to Using Stable Diffusion Forge UI
Explore the Stable Diffusion Forge UI, customizable settings, models, and more to enhance your image generation experience.

Kolonyalismo at Imperyalismo: Ang Kasaysayan ng Pagsakop sa Pilipinas
Tuklasin ang kasaysayan ng kolonyalismo at imperyalismo sa Pilipinas sa pamamagitan ni Ferdinand Magellan.

Mastering Inpainting with Stable Diffusion: Fix Mistakes and Enhance Your Images
Learn to fix mistakes and enhance images with Stable Diffusion's inpainting features effectively.

Pamamaraan at Patakarang Kolonyal ng mga Espanyol sa Pilipinas
Tuklasin ang mga pamamaraan at patakaran ng mga Espanyol sa Pilipinas, at ang epekto nito sa mga Pilipino.

How to Install and Configure Forge: A New Stable Diffusion Web UI
Learn to install and configure the new Forge web UI for Stable Diffusion, with tips on models and settings.
Found this summary useful?
Take it with you. One click puts it in your own LunaNotes library.
Save to LunaNotes